Achilles tendinitis, or Achilles tendinopathy, is pain and stiffness in the tendon at the back of the ankle, usually from load the tendon can't yet tolerate. It's common in runners, often stiffest first thing in the morning and sore after running. Management centres on adjusting training load and progressive calf and tendon strengthening.5,7
Ankle stiffness and pain when you wake up? A persistent ache that develops after harder running? You may be dealing with Achilles tendinopathy, a common problem for physically active people. Research suggests around 24% of athletes experience it during their careers, with runners having an incidence of about 9 injuries per 1,000 hours of running.1,5 This guide covers what Achilles tendinitis is, its symptoms and causes, the two main types, how it's assessed and treated, and how to keep running.
What is Achilles tendinitis?
Achilles tendinitis (also spelled tendonitis) is pain in the Achilles tendon, which connects your calf muscles to the heel bone. Clinicians now prefer the term Achilles tendinopathy, because persistent pain mainly reflects changes in tendon structure and load tolerance rather than ongoing inflammation. It's a load-related condition, most common in runners and jumping-sport athletes.5,9
The triceps surae is the group of calf muscles: gastrocnemius, soleus and plantaris. The Achilles tendon connects these muscles to the back of the heel (calcaneus). Research suggests part of what makes the tendon prone to injury is its less vascularised region, roughly 2–6 cm above where it attaches to the calcaneus.2,3
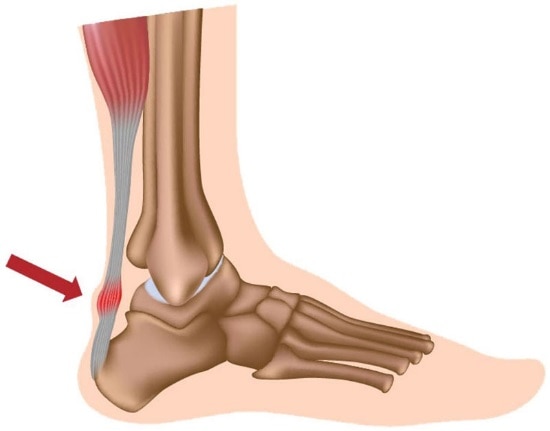
Jill Cook's continuum model suggests tendinopathy develops across three overlapping stages: reactive tendinopathy, tendon dysrepair and degenerative tendinopathy.9 A tendon that's suddenly exposed to more load than it's used to may react with pain and thickening. With repeated overload, structural changes can progress. It isn't well known at what age tendons become susceptible, and because tendon structure matures during puberty, Achilles tendinopathy can occur at any age.
What are the symptoms of Achilles tendinopathy?
Achilles tendinopathy symptoms usually include pain and stiffness at the back of the heel or lower calf, worst first thing in the morning or after sitting, that eases as you warm up then aches after activity. The tendon may be tender to squeeze and look or feel thickened, and pushing off can feel weaker.6,7
- Achilles pain: the hallmark symptom is persistent aching at the back of the heel or just above it, aggravated by activity and often worst on waking.
- Swelling and tenderness: swelling or thickening around the tendon may be noticed, and the tendon is often tender when squeezed.
- Stiffness and reduced push-off: the tendon is frequently stiffer and more uncomfortable in the early morning or after long periods of inactivity, and pain can reduce your ability to push off the ground.
What is the Achilles pinch test?
The "pinch test" generally refers to gently squeezing the tendon between finger and thumb to check for tenderness. In one study, pain on palpation of the tendon and reporting pain 2–6 cm above the heel were among the most valid clinical tests for mid-portion Achilles tendinopathy.11 It suggests tendinopathy but doesn't confirm it on its own, so it's part of a broader assessment.
Sudden pain with a snap or a feeling of being kicked in the back of the heel, followed by weakness, is different: that may be a rupture and needs prompt medical assessment.
What causes Achilles tendinitis?
Achilles tendinitis develops when the tendon is loaded beyond what it's conditioned for, most often through sudden spikes in running volume, speed or hills. Calf weakness or tightness, foot structure, higher body weight and metabolic factors may also reduce the tendon's tolerance. Usually it's a combination of these rather than one cause.4,5,7
- Excessive strain: physically active people such as runners and basketball and football players can overload the tendon, leading to pain and longer-term changes to tendon structure.
- Foot mechanics: variations in foot structure, such as arch shape, may increase the risk of developing Achilles tendinopathy.
- Sudden spikes in training load: a quick increase in training sessions, an inadequate warm-up and cool-down, or changes in technique during exercise can overload the Achilles tendon.
- Calf strength and flexibility: reduced calf strength or flexibility may increase loading through specific portions of the tendon.
- Body weight and metabolic health: higher body weight places more stress on the tendon, and metabolic conditions have been linked with mid-portion Achilles tendinopathy in runners.4
What is insertional Achilles tendinopathy?
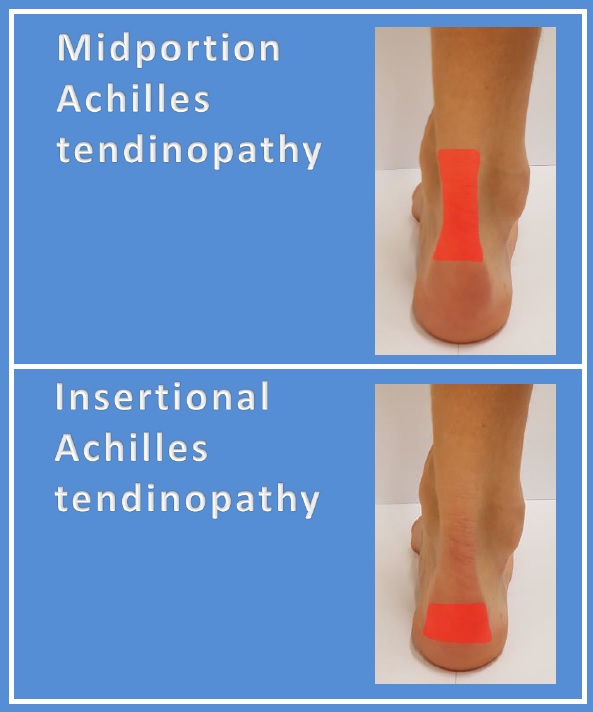
Insertional Achilles tendinopathy affects the lowest part of the tendon, roughly the last 2 cm where it attaches to the heel bone. Mid-portion tendinopathy affects the section about 2–6 cm above the heel. The distinction matters because exercises suited to mid-portion pain, such as deep heel drops off a step, can aggravate insertional pain.3,7
"Tendinitis" traditionally describes an acute, inflammatory-type presentation, while "tendinosis" describes longer-standing changes in tendon structure, often after repeated overload or an injury that hasn't fully recovered. "Tendinopathy" is the umbrella term that covers both.5,9 Anatomically, Achilles tendinopathy is divided into two types:
- Insertional Achilles tendinopathy: affects the distal portion of the tendon, approximately the last 2 cm, extending to its insertion into the calcaneus.
- Mid-portion Achilles tendinopathy: occurs in the middle third of the tendon, approximately 2–6 cm above the calcaneus.
How is Achilles tendinitis treated?
Achilles tendinitis treatment is primarily conservative and exercise-based. It commonly involves modifying aggravating activity rather than complete rest, a progressive calf and tendon loading program, and a gradual return to running. Rest alone tends not to improve longer-standing tendinopathy and can decondition the tendon and surrounding muscles.7,8
Understanding the tendon's function and the stage of the condition is important for management. In an early, reactive presentation, reducing aggravating load can settle pain, and some people use anti-inflammatory medication on the advice of their GP or pharmacist, alongside a graded rehab program. Longer-standing tendinopathy calls for a well-designed loading plan aimed at improving tendon capacity and function.
Footwear choices or a temporary heel lift may help reduce load on the tendon in the short term, particularly for insertional pain, as part of a broader plan.
Achilles tendinopathy exercises
Commonly used Achilles tendinopathy exercises progress from isometric calf holds, which may help settle pain, to slow heavy heel raises (straight and bent knee), eccentric heel lowers and, later, hopping and plyometrics. For insertional tendinopathy, heel raises are usually done on flat ground rather than dropping the heel off a step.7,8
- Isometric loading: the muscle contracts without the joint moving, for example holding a heel raise. These exercises load the tendon without much movement and are aimed at easing pain early on.
- Eccentric and heavy slow loading: eccentric exercises focus on the lowering phase of a contraction and may be gradually added. Examples include eccentric calf raises and seated soleus raises, progressing towards heavier, slower strength work.
- Energy-storage work: skipping, hopping and bounding are commonly reintroduced later to prepare the tendon for the spring-like demands of running.
Can I run with Achilles tendinitis?
Many runners can keep running with Achilles tendinitis if training is modified and symptoms are monitored. A randomised trial found people who continued running and jumping using a pain-monitoring model recovered as well as those who stopped. In that model, pain could reach a moderate level during activity but had to settle by the next morning.10
Managing how the tendon is reloaded during rehabilitation is important to reduce the risk of flare-ups. For those returning to running, several variables can be controlled to allow progressive reconditioning:
- Volume: reducing total volume and assessing the tendon's response allows load to be increased progressively. Tracking weekly load against what you've done in recent weeks, along with symptom and wellness monitoring, helps guide increases in running volume.
- Intensity: pace is often slower at first to reduce elastic loading through the tendon. Hills and speed work are usually reintroduced later.
- Frequency: frequency may be reduced initially to allow adaptation between runs, then gradually increased as volume builds.
- Surface and footwear: different surfaces and conditions change how much strain goes through the Achilles. Shoe choice and gradual adjustment to new terrain both matter.
- Cross-training: low-impact options such as cycling, swimming or anti-gravity treadmill running reduce Achilles loading while maintaining cardiovascular fitness.
A simple check is your morning stiffness: if it's worse the morning after a run than usual, the previous day's load was probably too much. Our physio for runners service and the RunLab running assessment, which includes running gait analysis, look at training load, calf strength and running mechanics together to plan your return.
How long does Achilles tendinopathy last?
Achilles tendinopathy recovery times vary considerably between people. Tendons adapt slowly, so rehabilitation is commonly measured in months rather than weeks, and outcomes depend on how long symptoms have been present, the type of tendinopathy and how consistently load is managed. Early management may help limit progression along the tendon continuum.9,10
In the pain-monitoring trial, both groups were still improving at 12-month follow-up,10 which is a useful reminder that tendon rehab is a long game. A holistic approach that looks at the factors that contributed in the first place (biomechanics, loading and strength) aims to reduce the risk of recurrence and optimise performance. If your heel pain sits under the heel rather than behind it, read our guide to plantar fasciitis; for shin pain, see shin splints.
FAQs
Can I run with Achilles tendinitis?
Often, yes, with modified training. In a randomised trial, people with Achilles tendinopathy who kept up running and jumping using a pain-monitoring model did as well as those who rested from those activities. Pain was allowed to reach a moderate level during activity, provided it settled by the next morning and wasn't trending worse week to week.
What is the Achilles pinch test?
The 'pinch test' usually means gently squeezing the Achilles tendon between finger and thumb to check for tenderness. Pain on palpation is one of the more useful clinical signs of Achilles tendinopathy, alongside pain 2–6 cm above the heel. It's not the same as the Thompson (calf squeeze) test, which checks for rupture.
How long does Achilles tendinopathy take to heal?
Recovery times vary widely and depend on how long you've had symptoms, the type of tendinopathy and how well load is managed. Tendons adapt slowly, so rehabilitation is commonly measured in months rather than weeks, and improvement often continues over a longer period.
Should I stretch a sore Achilles?
Calf stretching is commonly used, but for insertional Achilles tendinopathy, deep stretches that drop the heel below step level can compress the tendon against the heel bone and aggravate symptoms. Progressive strengthening is generally the main focus, with stretching adjusted to the type of tendinopathy.
Is it Achilles tendonitis, tendinitis or tendinopathy?
They describe the same problem. 'Tendonitis' and 'tendinitis' are spelling variants that imply inflammation. 'Tendinopathy' is the umbrella term clinicians now prefer, because long-standing Achilles pain mainly involves changes in tendon structure and load tolerance rather than ongoing inflammation.
When is Achilles pain an emergency?
If you feel a sudden snap or a sensation of being kicked in the back of the heel, followed by weakness pushing off or difficulty walking, seek medical assessment promptly. These are typical signs of an Achilles tendon rupture, which is managed differently from tendinopathy.
If you're experiencing Achilles pain or flare-ups, consider a physiotherapy consultation or a running injury assessment at our West End, Newstead or Woolloongabba clinics for tailored, data-driven guidance.
Book Now
References
- Colbert LH, Hootman JM, Macera CA. Physical activity-related injuries in walkers and runners in the aerobics center longitudinal study. Clin J Sport Med. 2000 Oct;10(4):259-63.
- O'Brien M. The anatomy of the Achilles tendon. Foot Ankle Clin. 2005 Jun;10(2):225-38.
- Mahan J, Damodar D, Trapana E, Barnhill S, Nuno AU, Smyth NA, Aiyer A, Jose J. Achilles tendon complex: The anatomy of its insertional footprint on the calcaneus and clinical implications. J Orthop. 2020 Jan-Feb;17:221-227
- Abate M, Salini V. Mid-portion Achilles tendinopathy in runners with metabolic disorders. Eur J Orthop Surg Traumatol. 2019 Apr;29(3):697-703.
- Longo UG, Ronga M, Maffulli N. Achilles Tendinopathy. Sports Med Arthrosc Rev. 2018 Mar;26(1):16-30.
- Maffulli N, Kenward MG, Testa V, Capasso G, Regine R, King JB. Clinical diagnosis of Achilles tendinopathy with tendinosis. Clin J Sport Med. 2003 Jan;13(1):11-5
- Vo TP, Ho GWK, Andrea J. Achilles Tendinopathy, A Brief Review and Update of Current Literature. Curr Sports Med Rep. 2021 Sep 01;20(9):453-461
- McClinton S, Luedke L, Clewley D. Nonsurgical Management of Midsubstance Achilles Tendinopathy. Clin Podiatr Med Surg. 2017 Apr;34(2):137-160
- Cook JL, Purdam CR. Is tendon pathology a continuum? A pathology model to explain the clinical presentation of load-induced tendinopathy. British Journal of Sports Medicine. 2009;43(6):409–416. doi:10.1136/bjsm.2008.051193
- Silbernagel KG, Thomeé R, Eriksson BI, Karlsson J. Continued sports activity, using a pain-monitoring model, during rehabilitation in patients with Achilles tendinopathy: a randomized controlled study. American Journal of Sports Medicine. 2007;35(6):897–906. doi:10.1177/0363546506298279
- Hutchison AM, et al. What is the best clinical test for Achilles tendinopathy? Foot and Ankle Surgery. 2013;19(2):112–117. doi:10.1016/j.fas.2012.12.006
Disclaimer: This blog is for informational purposes and should not be considered a substitute for professional medical advice. Please consult with our qualified healthcare providers for personalised recommendations related to your specific condition and needs.